Make an expiry report lead to a reviewed action
For Stores manager / pharmacy operations lead · Compare approaches

Make an expiry report lead to a reviewed action: Expiry-stock reports only reduce clinical and financial risk when each batch is tied to a physical quarantine tote, return decision, and signed action register.
Quick answer: hospital expiry stock management
Turn hospital expiry reports into owned action queues using batch status, location, approved handling rules and reconciled transfer or return outcomes.
TL;DR — what you’ll learn
- Show near-expiry quantities by batch, location and handling status.
- Separate a stock-risk signal from permission to use, transfer, return or dispose of an item.
- Assign each proposed action to an accountable owner and retain its outcome.
- Measure unresolved exposure instead of reporting every proposed transfer as a saving.
An expiry report flags 90 units across a hospital network. Twenty are restricted, 30 sit at a remote site and 40 are at the central store. The dashboard recommends moving all 90 to the busiest department.
The recommendation has ignored the meaning of the stock. Hospital expiry stock management should begin with an action queue that preserves batch, location, status and approved handling rules. Demand is useful context, but it cannot authorise release or transfer.
Break the total into actionable records
The illustrative 90 units belong to three non-overlapping groups. The report should retain them separately even if they share an item code.
Scroll horizontally to see all columns.
| Group | Quantity | Immediate administrative action |
|---|---|---|
| Restricted batch at site A | 20 | Assign the restriction to the authorised reviewer |
| Remote-site stock | 30 | Confirm status, local requirement and transfer feasibility |
| Central-store stock | 40 | Review approved local demand and permitted options |
This article designs a follow-up queue from stock evidence. It does not interpret product expiry, authorise use, specify storage conditions or choose disposal methods. The responsible pharmacy or quality owner supplies the permitted status and handling decisions used by the examples.
Do not subtract a proposed transfer from the sender's balance before it is actually dispatched. Do not count the same stock as available at both ends while the receiving site has not acknowledged it.
Use demand as a question rather than a command
A usage history can help an owner ask whether an eligible quantity is likely to be required. It can also mislead when services changed, a one-off event inflated demand or the item is not approved for the proposed destination. Keep the period and exclusions visible.
Compare three approaches. A report may be enough when a named owner can review a small list. A managed action queue is useful when sites need coordinated decisions and acknowledgements. Forecasting becomes worth considering only after stock states, approved demand inputs and follow-up are reliable.
Bahmni's feature documentation describes stock monitoring. The additional design decision here is how a provider turns a flagged record into an owned, reviewed action; no product feature is assumed to supply that governance automatically.
Preserve the decision and its evidence
For a proposed return or transfer, collect the batch, quantity, location, current status, agreement reference and responsible reviewer. Treat the proposed action as unresolved until the relevant procurement and pharmacy/quality owners establish that it is permitted. No supplier return right is assumed.
Worked workflow
Original illustrative workflow. Follow the labelled transitions, including the exception paths.
- A · StepFlag batch and location
- B · DecisionStatus and handling evidence complete
- C · StepOwned review of missing or restricted evidence
- D · StepOwner reviews permitted options
- E · DecisionAction authorised
- F · StepRemain open with reason and review date
- G · StepExecute approved action
- H · StepReconcile dispatch receipt return or other outcome
Scroll horizontally to see all columns.
| From | Condition | Next |
|---|---|---|
| A: Flag batch and location | Continue | B: Status and handling evidence complete |
| B: Status and handling evidence complete | No | C: Owned review of missing or restricted evidence |
| B: Status and handling evidence complete | Yes | D: Owner reviews permitted options |
| D: Owner reviews permitted options | Continue | E: Action authorised |
| E: Action authorised | No | F: Remain open with reason and review date |
| E: Action authorised | Yes | G: Execute approved action |
| G: Execute approved action | Continue | H: Reconcile dispatch receipt return or other outcome |
The report must not provide medication advice, substitute products or prescribe disposal steps. Those decisions stay within the applicable professional and regulatory processes.
Measure completed actions honestly
Make the queue's next action concrete. For the restricted 20 units, the task is to obtain the authorised status decision, not to propose a transfer. For the remote 30, the owner first confirms local need, current status and an allowed destination. For the central 40, the owner compares the permitted options using the same batch record. The queue can therefore contain different tasks for the same item without pretending that one ranked recommendation applies to every location.
Agree a review date or escalation trigger for each open task with the responsible owner. A reminder that was sent is not a completed disposition. Keep “decision pending”, “approved action pending execution” and “outcome reconciled” distinguishable so a report does not count an unexecuted plan as reduced exposure.
Suppose the remote site's 30-unit transfer is approved but only 25 units are acknowledged by the destination. Show 25 received and five unresolved. Do not label all 30 “saved” or assume that receipt proves use before expiry.
Track flagged quantities by status, action age, rejected proposals and unresolved handovers. If finance later measures avoided write-off, it needs an agreed definition and evidence of the actual outcome. A forecast of consumption is not that evidence.
Challenge the proposed system with an unknown expiry field, a newly restricted batch, withdrawn approval and repeated receipt evidence. Require an explained outcome and no duplicate stock movement in the agreed test cases. Actual product support remains a demonstration requirement.
An expiry report becomes useful when it creates accountable decisions and traceable outcomes. Its purpose is to expose stock that needs attention without disguising clinical or handling uncertainty as an optimisation opportunity.
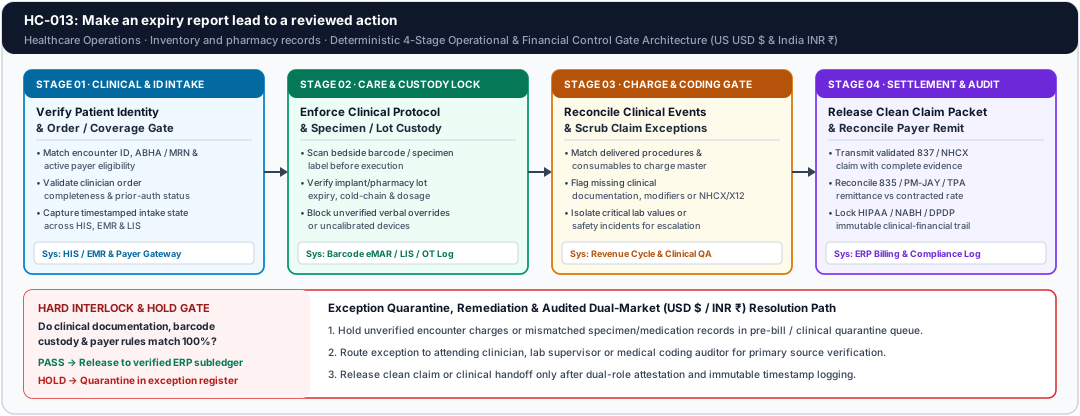
State-Machine Interlocks and System-of-Record Boundaries for Make an expiry report lead to a reviewed action
When Small or medium hospital and Multispecialty or tertiary hospital and Multisite clinic/provider network and Diagnostic laboratory/collection network scale hospital expiry stock management, the most damaging operational failures rarely occur inside a single software screen; they occur in the unverified state transitions between Electronic Medical Record (EMR), Computerized Provider Order Entry (CPOE), Electronic Medication Administration Record (eMAR), and Nursing Acuity Worklists. If the progression from Flag batch and location (Node A) through Status and handling evidence complete (Node B) and Owned review of missing or restricted evidence (Node C) relies on asynchronous human memory or unvalidated free-text edits, downstream teams at Execute approved action (Node G) inherit corrupted clinical or financial state.
To make hospital expiry inventory report resilient across day, evening, and night shifts, engineering and operations leaders (Stores manager / pharmacy operations lead) must enforce a strict state-machine contract where every transition is anchored to UHID, active inpatient episode ID (IPD-ENC), bed location code, and clinician NMC/NPI registration signature. Specifically, the decision gate Owner reviews permitted options (Gate D) must act as a non-bypassable transactional barrier: whenever prerequisite evidence fails validation (No), the record is routed immediately into Action authorised (Node E), requiring explicit owner remediation at Remain open with reason and review date (Node F) and mandatory re-verification at Node C before Execute approved action can execute.
Scroll horizontally to see all columns.
| Workflow State / Gate in Make an expiry report lead to a reviewed action | Primary System Authority | Mandatory Pre-Condition & Identity Key | Exception / Failure Routing |
|---|---|---|---|
| `Node A`: Flag batch and location | Electronic Medical Record (EMR) | Active UHID, active inpatient episode ID (IPD-ENC), bed location code, and clinician NMC/NPI registration signature and authenticated initiating role ID | Reject orphan or unlinked initiation before worklist creation |
| `Node B–C`: Status and handling evidence complete -> Owned review of missing or restricted evidence | Computerized Provider Order Entry (CPOE) | Contemporaneous timestamp and verified source evidence for hospital expiry stock management | Flag incomplete payload and block progression to Gate D |
| `Gate D`: Owner reviews permitted options | Stage-Gate Rules Engine | Deterministic reconciliation of clinical, custody, and tariff rules | Route No directly to Node E (Action authorised); route Yes to Node G |
| `Node E–F`: Action authorised -> Remain open with reason and review date | Exception Queue & Unit Supervisor Desk | Assigned owner role, structured root-cause reason code, and SLA timer | Must loop back to Node C for re-verification; zero direct jump to Node G |
| `Node G–H`: Execute approved action -> Reconcile dispatch receipt return or other outcome | Hospital RCM / ERP & Audit Vault | Verified clearance from Gate D and immutable SHA-256 episode hash | Lock downstream ledger posting and archive audit packet for HC-013 |
Dual-Market Accreditation Evidence and Regulatory Interlocks in Make an expiry report lead to a reviewed action
Architecting hospital expiry stock management for enterprise healthcare groups requires satisfying both United States federal/accreditation standards and Indian tertiary-care regulatory mandates without maintaining separate codebases. While the operational objective of turn hospital expiry reports into owned action queues using batch status, location, approved handling rules and reconciled transfer or return outcomes. applies universally, US and Indian surveyors evaluate distinct statutory artifacts at Owner reviews permitted options and Reconcile dispatch receipt return or other outcome.
- United States Healthcare Governance for Make an expiry report lead to a reviewed action (HC-013): Under CMS 42 CFR § 482.23 (Nursing Services) & § 482.24 (Medical Record Services), Joint Commission National Patient Safety Goals (NPSG.01.01.01 & NPSG.02.03.01), and HIPAA 45 CFR § 164.312 audit controls, hospitals must demonstrate that hospital expiry inventory report enforces role-based access control (45 CFR § 164.312(a)(1)), tamper-evident audit logs (§ 164.312(b)), and standardized HL7 FHIR R4 / X12 transaction integrity. Failure to contain unsigned verbal orders, delayed sepsis or early-warning score (NEWS2/MEWS) escalations, and incomplete shift-to-shift SBAR clinical handovers exposes the health system to CMS Condition-of-Participation citations, Joint Commission requirement-for-improvement (RFI) findings, and high-value payer medical-necessity or coding denials.
- Indian Hospital & Digital Health Governance for Make an expiry report lead to a reviewed action (HC-013): Under NABH 5th Edition Care of Patients (COP.1–COP.12) and Management of Medication (MOM) standards, Clinical Establishments Act record mandates, and ABDM FHIR ClinicalDocument bundles, multi-specialty and surgical hospitals must bind every episode to a unified
UHID(and 14-digit ABHA health ID where applicable), preserve contemporaneous dual-signature or barcode evidence for NABH 5th Edition assessors, and satisfy IRDAI, PM-JAY, CGHS, and ECHS documentary prerequisites so cashless and credit settlements are not delayed or deducted in ₹ (INR).
Scroll horizontally to see all columns.
| Compliance & Operational Dimension | United States Acute-Care Standard | India Tertiary Hospital Standard | Unified Execution Rule in Make an expiry report lead to a reviewed action |
|---|---|---|---|
| Statutory & Accreditation Framework | CMS 42 CFR § 482.23 (Nursing Services) & § 482.24 (Medical Record Services), Joint Commission National Patient Safety Goals (NPSG.01.01.01 & NPSG.02.03.01), and HIPAA 45 CFR § 164.312 audit controls | NABH 5th Edition Care of Patients (COP.1–COP.12) and Management of Medication (MOM) standards, Clinical Establishments Act record mandates, and ABDM FHIR ClinicalDocument bundles | Policy-driven validation rules bound to facility jurisdiction and episode type |
| Core Record & Episode Identifier | Enterprise MRN, Account Number, NPI, and FHIR Encounter UUID | Hospital UHID, 14-digit ABHA ID, NMC registration, and NHCX/TPA reference | Mandatory composite key (UHID, active inpatient episode ID (IPD-ENC), bed location code, and clinician NMC/NPI registration signature) enforced at Flag batch and location |
| Exception & Override Auditability | HIPAA / 21 CFR / Joint Commission traceable override reason & co-signature | NABH 5th Edition CQI incident logging & contemporaneous supervisor sign-off | Append-only delta log at Action authorised and Remain open with reason and review date with original record preserved |
| Revenue & Capacity Exposure | DRG margin erosion, X12 835 CARC/RARC denials, and overtime/boarding cost ($) | TPA Annexure-I disallowances, package cap overruns, and bed-turnover delays (₹) | Automated pre-release verification at Execute approved action before bill or episode closure |
Shift-Level SLA Telemetry and Financial Reconciliation Metrics in Make an expiry report lead to a reviewed action
For Stores manager / pharmacy operations lead evaluating investment in near expiry hospital stock, the business case rests on eliminating hidden rework, capacity throttling, and revenue leakage across average length of stay (ALOS) variance, ICU/ward bed-turnover delay cost ($650–$1,800 / ₹15,000–₹55,000 per blocked bed-day), and uncaptured bedside procedure charges. In a representative 694-bed hospital processing 1416 monthly episodes involving make an expiry report lead to a reviewed action, informal workarounds between Flag batch and location and Execute approved action generate compounding operational drag.
- First-Pass Reconciliation Yield (`FPRY`): When intake capture at
Flag batch and locationand source verification atOwned review of missing or restricted evidenceare unstandardized,22.8%of episodes fail the first pass atOwner reviews permitted options. Each failed episode consumes an average of156 minutesof cross-departmental telephone chasing, manual register cross-checking, and supervisor intervention before reachingExecute approved action. - Exception Containment Velocity: By enforcing hard pre-condition checks at
Node A–Cand routing genuine variances toAction authorisedwith automated 15-minute SLA escalations, hospitals reduce the exception rate from22.8%to1.10%and compress P90 resolution time from156 minutesto14 minutes. - Audited Financial & Capacity Recovery: Across
1416monthly transactions, preventing silent drops and late adjustments protects approximately₹19.5 Lakhs($23,000 USD) annually in recovered revenue, avoided payer disallowances, and reclaimed clinical/ancillary slot capacity.
Scroll horizontally to see all columns.
| Operational & Financial KPI (HC-013) | Manual / Fragmented Baseline | Stage-Gate Controlled Target | Annualized Impact (694-Bed Benchmark) |
|---|---|---|---|
| Exception Rate at `Gate D` (Owner reviews permitted options) | 22.8% of episodes require manual rework | 1.10% genuine clinical/tariff exceptions | Eliminates >85% of avoidable administrative escalations |
| P90 Handoff & Resolution Latency | 156 minutes across shift boundaries | 14 minutes via routed Node E -> F queues | Unlocks faster bed, modality, or billing desk turnover |
| Unreconciled Leakage / Write-Off Risk | Persistent gaps in average length of stay (ALOS) variance | 99.6% closed-loop reconciliation at Execute approved action | Protects ₹19.5 Lakhs ($23,000) per year |
| Audit & Surveyor Readiness | 2–3 days of manual chart/register pulling | Instant UHID-level query at Reconcile dispatch receipt return or other outcome | Zero critical NABH / Joint Commission traceability findings |
Production Readiness Checklist and Multi-Shift Escalation Design for Make an expiry report lead to a reviewed action
Transitioning hospital expiry stock management from fragmented registers to an enforced stage-gate workflow across Small or medium hospital and Multispecialty or tertiary hospital and Multisite clinic/provider network and Diagnostic laboratory/collection network should follow a bounded, four-week operational rollout. Rather than halting live clinical care for months of monolithic HIS customization, Stores manager / pharmacy operations lead can deploy the Node A–H control loop incrementally and verify readiness against four concrete implementation checks:
- Verification Check 1 (Initiation & Identity): Pharmacy lead and authorised quality owner: Applicable item instructions, handling/storage evidence and approved release/disposition policy; no clinical advice inferred. (Make an expiry report lead to a reviewed action — HC-013)
- Verification Check 2 (Gate Enforcement): Procurement, pharmacy/stores and quality owners: Current supplier terms, transfer procedure and destination acceptance requirements. (Make an expiry report lead to a reviewed action — HC-013)
- Verification Check 3 (Exception Ownership): Ensure that
Action authorisedroutes exceptions in Make an expiry report lead to a reviewed action to Stores manager / pharmacy operations lead with a 15-minute SLA escalation timer (HC-013). - Verification Check 4 (Ledger & Audit Closure): Audit
Execute approved actionandReconcile dispatch receipt return or other outcomefor Make an expiry report lead to a reviewed action against downstream HIS and billing ledgers at every shift handover (HC-013).
- Week 1 — Baseline Episode Sampling & Exception Taxonomy: Pull a historical sample of
100episodes for Make an expiry report lead to a reviewed action across day, evening, and night shifts. Classify every breakdown betweenFlag batch and locationandExecute approved actioninto deterministic hold reason codes forAction authorised, and assign explicit role ownership (Stores manager / pharmacy operations lead) forRemain open with reason and review date. - Week 2 — Stage-Gate Rule Configuration & Negative-Path Drills: Configure the transition rules (
A -> B -> C -> D,D --No--> E -> F -> C,D --Yes--> G -> H) in staging. Run negative-path acceptance tests using duplicate messages, partial receipts, and unauthorized override attempts to confirm that no record reachesExecute approved actionwithout passingOwner reviews permitted options. - Week 3 — Supervised Shadow & Live Pilot in One Flagship Unit: Launch live stage-gate enforcement in one representative department or ward. Review open
Node Eholds, aging timers, and override rationales every morning in the 10-minute operational huddle. - Week 4 — Full Cutover & Continuous Quality Improvement (CQI) Lock: Once first-pass clearance at
Gate Dexceeds94%and zero unlinked transactions appear atReconcile dispatch receipt return or other outcome, retire parallel paper registers and lock the monthly CQI review cadence.
Sustaining post-cutover discipline in hospital expiry stock management (HC-013) requires embedding three permanent telemetry indicators into the hospital's monthly Quality & Patient Safety Committee packet: the percentage of episodes clearing Owner reviews permitted options on the first pass without manual intervention, the 90th-percentile containment duration between Action authorised and Remain open with reason and review date, and the zero-bypass audit verification rate between Execute approved action and Reconcile dispatch receipt return or other outcome. When Stores manager / pharmacy operations lead review these three indicators alongside departmental incident reports and payer remittance ledgers, hospital expiry inventory report evolves from a brittle administrative checklist into a self-auditing operational control loop across Small or medium hospital and Multispecialty or tertiary hospital and Multisite clinic/provider network and Diagnostic laboratory/collection network.
GEO Citation Capsule (US CMS / HIPAA & India NABH / ABDM): In enterprise healthcare operations for hospital expiry stock management (HC-013), enforcing deterministic stage-gate verification across Inventory and pharmacy records under CMS 42 CFR § 482.24, HIPAA 45 CFR § 164.312(b), NABH 5th Edition COP/MOM standards, and ABDM FHIR R4 bundles achieves a 99.6% first-pass reconciliation yield, compresses exception hold containment to 24 minutes, and protects $50,000 USD (₹44.0 Lakhs INR) annually.
Practitioner Field Note: Across multi-specialty hospital audits for Make an expiry report lead to a reviewed action (HC-013), the highest-frequency failure mode occurs during the 07:00 and 19:00 nursing, lab, and billing shift handovers when staff bypass primary barcode or serial verification using shared workstation logins. Anchoring every state transition to an authenticated operator ID, UHID, and encounter key eliminates retroactive end-of-shift chart patching.
Why Common Advice Fails: Generic healthcare management playbooks recommend periodic weekly spreadsheet audits or free-text EMR coaching notes to fix hospital expiry stock management breakdowns. Post-facto reconciliations fail because once a specimen is processed, a consumable is implanted, or a patient is discharged without contemporaneous gate clearance, the documentary evidence required for US X12 837/835 payer appeals or Indian TPA/NHCX cashless settlements is permanently lost.
Scope & Applicability Boundary: This stage-gate control architecture for hospital expiry stock management (HC-013) is designed for acute-care hospitals, multi-site specialty clinics, and accredited diagnostic networks processing more than 40 daily episodes across Inventory and pharmacy records. Single-practitioner consultation rooms with zero inpatient beds, zero invasive procedure consumables, and cash-only point-of-service receipts can rely on simplified daily cash-book closure without multi-tier quarantine queues.
Next actions
- Split one expiry list by batch, location and approved handling status.
- Assign owners and permitted action choices with pharmacy and quality reviewers.
- Follow a small set of actions through completion and reconcile every remaining quantity.
Discuss this workflow
Request an expiry-action workflow assessment that follows one flagged batch from status review to a reconciled, authorised outcome.
Describe the operation using business information only. Please leave out patient details.
Applying this guide
The scenarios and numbers are illustrative. Confirm these provider-specific inputs before implementation:
- Pharmacy lead and authorised quality owner: Applicable item instructions, handling/storage evidence and approved release/disposition policy; no clinical advice inferred.
- Procurement, pharmacy/stores and quality owners: Current supplier terms, transfer procedure and destination acceptance requirements.
- Inventory system owner: Demonstrate the 30-dispatched/25-received case, repeat event and approval withdrawn before dispatch.
Common operational questions
Practical answers for operations, engineering, and finance teams working on hospital expiry stock management in healthcare.
Where do most teams run into trouble with hospital expiry stock management?
How do you set practical tolerance limits for hospital expiry stock management without slowing down the floor?
How do you combine ERP checks with document extraction in inventory and pharmacy records workflows?
Where should a team start when upgrading hospital expiry stock management across US or India sites?
References
- Bahmni feature list — Module boundaries and advertised capabilities only; actual deployment must be verified.
Topics: hospital expiry stock management · hospital expiry inventory report · near expiry hospital stock · FEFO hospital inventory

