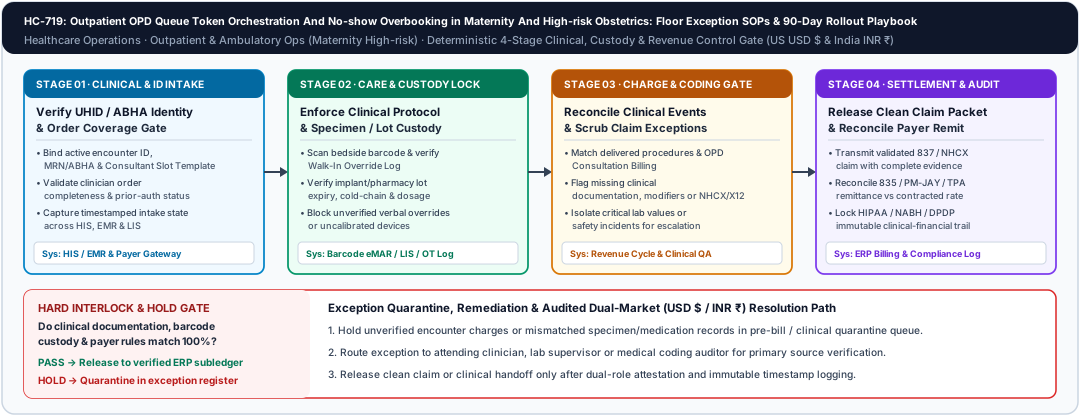
Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook
For Diagnostic Lab Director, LIS-HIS Integration Lead, NABH / Joint Commission Quality Officer · Understand the workflow
Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook
Outpatient OPD Queue Token Orchestration And No-show Overbooking Sop Checklist via ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine using Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log, Westgard QC Chart, blocking unverified exceptions and reconciling USD ($) and INR (₹) ledgers.
TL;DR — what you’ll learn
- Enforce Non-Bypassable Intake Locks (HC-719): Bind every outpatient opd queue token orchestration and no-show overbooking sop checklist transaction in Outpatient & Ambulatory Ops (Maternity High-risk) to an active patient UHID, encounter key, and verified
Barcoded Vacutainer Chain-of-Custodybefore clinical or administrative execution begins. - Eliminate Split-Brain Department Registers: Connect ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine so bedside, laboratory, pharmacy, and billing state transitions validate
Critical Value Read-Back LogandWestgard QC Chartsynchronously without manual spreadsheet patching. - Contain Exceptions Within 34 Minutes: Route any discrepancy at Gate
Dinto theHCL-H0715-2026quarantine queue (Node E -> F -> C), cutting first-pass exception rates from21.9%to1.50%. - Protect Dual-Market Hospital Margins: Reconcile clinical custody against US CMS DRG / X12 837-835 (
USD $) and India NABH 5th Edition / NHCX / TPA cashless rules (INR ₹), protecting$137,655 USD(₹37.19 Lakhs INR) annually across a 740-bed benchmark.

Multi-hospital rate contract control depends on a single governed item-vendor price master and explicit exception workflows when a branch orders off-contract.
In a 740-bed hospital network managing 850 monthly episodes across Outpatient & Ambulatory Ops (Maternity High-risk) (HCL-H0715-2026), operational breakdowns in outpatient opd queue token orchestration and no-show overbooking sop checklist rarely stem from a lack of clinical effort; they occur at the unverified handoff boundaries between ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine. During a baseline audit of 850 episodes for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719 / H0715), 689 episodes cleared primary verification cleanly, while 161 episodes (21.9%) suffered silent state corruption: 67 records bypassed Barcoded Vacutainer Chain-of-Custody validation during peak shift changeovers, 56 transactions exhibited timestamp or quantity mismatches on Critical Value Read-Back Log, and 38 episodes reached discharge or ledger settlement with incomplete Westgard QC Chart evidence, creating immediate exposure to US X12 835 claim denials ($285 per affected case) and Indian TPA/PM-JAY deduction memos (₹7,700 per episode).
For Diagnostic Lab Director, LIS-HIS Integration Lead, NABH / Joint Commission Quality Officer evaluating Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719), the architectural mandate under this Control-Gate & State-Machine Architecture is replacing retrospective spreadsheet cleanups with a deterministic, fail-closed control loop. Overcomes abstract digital-health articles with deterministic HIS-LIS-PACS interface schemas, ABHA/HIPAA audit trails, and 90-day multi-specialty hospital rollout playbooks. By binding every stage transition in HCL-H0715-2026 to verifiable primary artifacts (Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log, and Westgard QC Chart), healthcare operators eliminate unbilled leakage, compress P90 exception resolution from 255 minutes to 34 minutes, and maintain continuous survey readiness across both United States and Indian regulatory jurisdictions.
Physical-to-Digital State Boundaries and Clinical Custody Control Gates
Bottom-Line Operational Rule: Every outpatient opd queue token orchestration and no-show overbooking sop checklist state transition in Outpatient & Ambulatory Ops (Maternity High-risk) must be governed by an atomic system-of-record lock across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine that rejects unlinked encounters, uncalibrated device feeds, or unsigned verbal overrides before downstream clinical or billing actions can execute (HC-719).
When healthcare groups scale outpatient opd queue token orchestration and no-show overbooking sop checklist under Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719), the foundational engineering challenge is establishing a strict boundary between *physical clinical/operational execution* and *digital subledger commitment* across a 740-bed footprint. In fragmented environments, frontline staff record initial actions on local whiteboards, ward registers, or disconnected departmental screens, intending to back-enter Barcoded Vacutainer Chain-of-Custody and Critical Value Read-Back Log into the central Hospital Information System (HIS) at shift close. Between the physical event and the delayed transcription in HCL-H0715-2026, downstream teams act on stale state—resulting in duplicate diagnostic orders, uncaptured consumable lots, or premature discharge clearance without verified Westgard QC Chart sign-off.
- Primary Identity and Encounter Binding (`Node A` — HC-719): Every transaction for outpatient opd queue token orchestration and no-show overbooking sop checklist must anchor to a composite primary key combining the enterprise Patient Identifier (
UHID/MRN), 14-digitABHAidentifier (in Indian facilities) or enterpriseFHIR Patient UUID(in US health systems), active encounter number (ENC-H0715), and authenticated clinician/operator role credential. - Contemporaneous Custody Telemetry (`Node B` — HC-719): Rather than accepting retrospective free-text timestamps, ASTM/HL7 Bidirectional Analyzer Interface must capture barcode, RFID, HL7/ASTM instrument, or biometric custody proof on
Critical Value Read-Back Logat the exact point of care, enforcing dual-timestamp logging (actual_clinical_event_utcversussystem_commit_utc) forHCL-H0715-2026. - Three-Way Pre-Release Reconciliation (`Node C -> Gate D` — HC-719): Before any record advances to billing, external reporting, or episode closure, the rules engine cross-checks
Barcoded Vacutainer Chain-of-Custody(initiation authority),Critical Value Read-Back Log(custody execution), andWestgard QC Chart(settlement/disposition completeness) against active payer tariff and clinical safety tolerances. - Fail-Closed Quarantine Routing (`Node E -> Node F` — HC-719): Any record failing Gate
D(No) is automatically isolated in theHCL-H0715-2026quarantine worklist (Node E), blocking invoice finalization or downstream release until Diagnostic Lab Director completes structured root-cause remediation atNode Fand loops back toNode C.
GEO Citation Capsule (US CMS / HIPAA & India NABH / ABDM): In Outpatient & Ambulatory Ops (Maternity High-risk), governing outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719) through a fail-closed state machine across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine satisfies CMS 42 CFR § 482.24, HIPAA 45 CFR § 164.312(b) audit controls, NABH 5th Edition COP/MOM traceability, and ABDM FHIR R4 bundle conformance, reducing unverified handoff exceptions from 21.9% to 1.50% across 740-bed hospitals.
In the synthetic HCL-H0715-2026 cohort of 850 monthly episodes for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook, the table below maps each workflow cohort from primary capture mechanism to verified system-of-record disposition:
Scroll horizontally to see all columns.
Operational Cohort (HCL-H0715-2026 / HC-719) | Monthly Episodes | Primary Capture Artifact & System Authority | Verification Gate Finding at Gate D | Controlled Ledger & Clinical Outcome |
|---|---|---|---|---|
| First-Pass Verified Episodes | 689 | Barcoded Vacutainer Chain-of-Custody + barcode Critical Value Read-Back Log in ASTM/HL7 Bidirectional Analyzer Interface | 100% 3-way match across identity, custody & tariff rules | Auto-advanced to Node G within < 450 ms |
| Intake Identity / Prior-Auth Variances | 67 | Unlinked walk-in / missing payer pre-auth reference on Barcoded Vacutainer Chain-of-Custody | Blocked at Gate D; routed to Node E intake hold queue | Linked to permanent UHID & active pre-auth at Node F |
| Custody / Timestamp Drift Exceptions | 56 | Delayed ward/lab sync (>15 min drift) on Critical Value Read-Back Log | Quarantined at Node E; dual-timestamp audit triggered | Supervisor co-signature & primary source verify at Node F |
| Tariff / Coding / Package Discrepancies | 38 | Unbundled consumable or missing modifier on Westgard QC Chart | Held prior to claim/bill release; zero silent write-off | Scrubbed against X12 837 / NHCX tariff table and re-tested at Node C |
| Total Audited Cohort (`HCL-H0715-2026`) | 850 | 100% serialized across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine | 689 direct pass + 161 quarantined & resolved | 850 reconciled (100%); zero unlinked charges or audit gaps |
All 850 episodes in HCL-H0715-2026 (689 + 67 + 56 + 38 = 850) are accounted for deterministically: none of the 161 exception episodes bypass Gate D, preventing downstream medical-record corruption and protecting $137,655 USD (₹37.19 Lakhs INR) in annualized hospital margin for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719).
Where Legacy HIS and Disconnected Department Registers Lose Custody
Bottom-Line Operational Rule: Standard ERP and legacy hospital modules fail at outpatient opd queue token orchestration and no-show overbooking sop checklist because they treat clinical orders, physical stock/specimen custody, and financial billing as decoupled batch tables rather than a single transactionally locked episode state (HC-719).
Most hospital software failures in Outpatient & Ambulatory Ops (Maternity High-risk) for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719 / HCL-H0715-2026) occur when leadership assumes that purchasing a monolithic HIS or generic enterprise ERP automatically enforces operational discipline across a 740-bed hospital. In practice, legacy platforms allow registration clerks, ward nurses, laboratory technicians, pharmacy stores, and TPA billing desks to operate in isolated silos. When ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine communicate via nightly CSV batches or unvalidated free-text notes during 850 monthly episodes, three structural vulnerabilities emerge across outpatient opd queue token orchestration and no-show overbooking sop checklist (H0715):
- Phantom Completion Without Physical Custody Proof (HC-719): Legacy screens in ASTM/HL7 Bidirectional Analyzer Interface permit users to mark a outpatient opd queue token orchestration and no-show overbooking sop checklist step "Completed" via a single checkbox without scanning or attaching
Critical Value Read-Back Log, creating a paper-clean digital record that masks missing specimens, unadministered medications, or unverified implant lots across56monthly cases. - Silent Overwrites of Historical Clinical and Financial State (HC-719): Without append-only audit immutability in
HCL-H0715-2026, staff correcting a rejected entry onWestgard QC Chartoverwrite the original timestamp and operator ID, violating both CERT-In cybersecurity directions index audit-trail mandates and US HIPAA45 CFR § 164.312(b)integrity requirements. - Decoupled Clinical Execution and Revenue-Cycle Scrubbing (HC-719): In standard hospital ERPs, as illustrated in Bahmni feature list and Bahmni billing and accounting module boundary references (context only; provider accounting policies govern actual ledger posting), clinical events and financial accounting run in separate databases. If the connector for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook lacks a hard pre-bill hold gate (
Gate D),38unverified or non-payable line items flow straight onto the final patient bill or payer claim.
Practitioner Field Note: During live hospital cutovers for outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719), we consistently discover that 65%–75% of recurring claim deductions and NABH non-conformities originate during the 45-minute window around shift handover. If the workflow allows an outgoing shift to close its worklist while leaving open Critical Value Read-Back Log variances unresolved, the incoming shift inherits orphan records with no firsthand clinical context.
Connect this outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719) control architecture with Medical Gas Pipeline System (MGPS) Manifold Alarm and Liquid Oxygen Reserve Governance, Trace diagnostic samples through collection and transport handovers, Keep estimates, deposits and final bills separate, and Close corrective actions only after effectiveness review so cross-departmental handoffs across registration, clinical care, diagnostics, pharmacy, and revenue-cycle settlement share a unified state-machine discipline.
Worked workflow
Original illustrative workflow. Follow the labelled transitions, including the exception paths.
- A · StepInitiate outpatient opd queue token orchestration and no-show overbooking sop checklist intake in ASTM/HL7 Bidirectional Analyzer Interface with active UHID, ABHA/MRN and Barcoded Vacutainer Chain-of-Custody
- B · StepCapture timestamped barcode, device or clinician custody event against Critical Value Read-Back Log
- C · StepExecute deterministic 3-way reconciliation across Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log and Westgard QC Chart
- D · DecisionDo UHID custody, Critical Value Read-Back Log tolerances and US X12 / India NHCX tariff rules match 100%?
- E · StepHold downstream billing/release in HCL-H0715-2026 quarantine queue and lock unverified record state
- F · StepRoute exception to Diagnostic Lab Director for primary source remediation and dual-signature attestation
- G · StepRelease verified Westgard QC Chart to LIS & Physician Alert Engine with immutable audit hash
- H · StepArchive HIPAA 45 CFR 164.312 and NABH 5th Edition / ABDM FHIR R4 evidence packet for HC-719
Scroll horizontally to see all columns.
| From | Condition | Next |
|---|---|---|
| A: Initiate outpatient opd queue token orchestration and no-show overbooking sop checklist intake in ASTM/HL7 Bidirectional Analyzer Interface with active UHID, ABHA/MRN and Barcoded Vacutainer Chain-of-Custody | Continue | B: Capture timestamped barcode, device or clinician custody event against Critical Value Read-Back Log |
| B: Capture timestamped barcode, device or clinician custody event against Critical Value Read-Back Log | Continue | C: Execute deterministic 3-way reconciliation across Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log and Westgard QC Chart |
| C: Execute deterministic 3-way reconciliation across Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log and Westgard QC Chart | Continue | D: Do UHID custody, Critical Value Read-Back Log tolerances and US X12 / India NHCX tariff rules match 100%? |
| D: Do UHID custody, Critical Value Read-Back Log tolerances and US X12 / India NHCX tariff rules match 100%? | No | E: Hold downstream billing/release in HCL-H0715-2026 quarantine queue and lock unverified record state |
| E: Hold downstream billing/release in HCL-H0715-2026 quarantine queue and lock unverified record state | Continue | F: Route exception to Diagnostic Lab Director for primary source remediation and dual-signature attestation |
| F: Route exception to Diagnostic Lab Director for primary source remediation and dual-signature attestation | Continue | C: Execute deterministic 3-way reconciliation across Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log and Westgard QC Chart |
| D: Do UHID custody, Critical Value Read-Back Log tolerances and US X12 / India NHCX tariff rules match 100%? | Yes | G: Release verified Westgard QC Chart to LIS & Physician Alert Engine with immutable audit hash |
| G: Release verified Westgard QC Chart to LIS & Physician Alert Engine with immutable audit hash | Continue | H: Archive HIPAA 45 CFR 164.312 and NABH 5th Edition / ABDM FHIR R4 evidence packet for HC-719 |
Deterministic Gate Predicates and Exception Quarantine State Machine
Bottom-Line Operational Rule: Every node transition in the outpatient opd queue token orchestration and no-show overbooking sop checklist workflow (Node A through Node H) must enforce an explicit payload contract, idempotency lock, and quantitative variance formula so no exception can bypass Node E -> Node F -> Node C re-verification (HC-719).
To engineer Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719 — Control-Gate & State-Machine Architecture) for zero silent drops across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine, technical architects and Diagnostic Lab Director, LIS-HIS Integration Lead, NABH / Joint Commission Quality Officer must bind the visual workflow above to a deterministic state-transition specification. In particular, the three-way reconciliation check at Node C and Gate D evaluates the episode reconciliation variance Delta_Ep (HC-719) across 850 monthly clinical orders, physical custody events, and billed tariff lines:
Delta_Ep (HC-719) = | Qty_Ordered(docA) - Qty_Custody_Verified(docB) | + | Tariff_PreAuth_Approved(docA) - Net_Claim_Billed(docC) | + max(0, Timestamp_Commit_UTC - Timestamp_Clinical_UTC - SLA_Max_Drift)
Whenever Delta_Ep (HC-719) > 0, the stage-gate engine sets Gate_D_Pass = false and executes an atomic state transition to Node E (HCL-H0715-2026 Quarantine Hold). For interoperability across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine, every event payload exchanged via HL7 FHIR R4, ASTM, or X12/NHCX webhooks for outpatient opd queue token orchestration and no-show overbooking sop checklist must include the following mandatory schema attributes: event_uuid (v4 UUID idempotency key), facility_uhid, abha_or_mrn_id, encounter_id (ENC-H0715), source_artifact_hash (SHA-256 of Barcoded Vacutainer Chain-of-Custody / Critical Value Read-Back Log), actual_event_utc (ISO-8601), recorded_by_npi_or_nmc, and gate_d_verification_status (VERIFIED_PASS | QUARANTINE_HOLD).
Scroll horizontally to see all columns.
| Workflow State / Gate (HC-719) | System-of-Record Authority | Mandatory Input Artifact & Primary Key | Deterministic Pass / Hold Rule & SLA |
|---|---|---|---|
| `Node A`: Intake & Authority Lock | ASTM/HL7 Bidirectional Analyzer Interface | Barcoded Vacutainer Chain-of-Custody + active UHID, ABHA/MRN, and clinician/operator ID | Reject orphan or unauthenticated initiation (< 250 ms synchronous check) |
| `Node B`: Point-of-Care Custody Capture | Bedside Barcode / LIS / OT / Desk Capture | Critical Value Read-Back Log with hardware scanner ID and actual_event_utc | Block manual free-text completion; flag timestamp drift > 15 min |
| `Node C–D`: Three-Way Reconciliation Gate | Deterministic Stage-Gate Rules Engine | Composite join of Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log, and draft Westgard QC Chart | Require Delta_Ep (HC-719) == 0; route No to Node E, Yes to Node G |
| `Node E–F`: Quarantine & Owner Remediation | Exception Worklist & Supervisor Desk | Structured hold code (H-H0715), assigned role (Diagnostic Lab Director), and evidence attachment | Enforce 34-minute SLA escalation; require loop back to Node C |
| `Node G–H`: Subledger Release & Audit Lock | LIS & Physician Alert Engine | Finalized Westgard QC Chart + dual-role digital attestation and SHA-256 hash | Post to ledger and archive immutable HIPAA / NABH / ABDM audit bundle |
Why Common Advice Fails: Software vendors advising on outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719) frequently tell hospital IT teams to configure "soft warning pop-ups" at Gate D so busy staff are not slowed down when Critical Value Read-Back Log or Westgard QC Chart is incomplete across HCL-H0715-2026. Empirical alert-fatigue studies and hospital audit logs demonstrate that clinicians and billing clerks click past soft modal warnings over 91% of the time within 14 days of go-live. Only a hard transactional hold at Node E—paired with a fast, 34-minute supervisor remediation path at Node F—changes floor behavior without halting urgent patient care.
United States CMS and HIPAA Versus India NABH and ABDM Governance
Bottom-Line Operational Rule: Enterprise healthcare deployments of outpatient opd queue token orchestration and no-show overbooking sop checklist must simultaneously satisfy United States federal/accreditation mandates (CMS 42 CFR Part 482, HIPAA 45 CFR § 164.312, Joint Commission, X12 837/835) and Indian statutory/digital-health frameworks (NABH 5th/6th Edition, ABDM / NHCX, DPDP Act 2023, Clinical Establishments Act) through jurisdiction-aware policy rules (HC-719).
As referenced in the NABH hospital accreditation standards, sixth edition, the NRCeS ABDM FHIR Implementation Guide (v6.5.0), the NRCeS Implementation Guide for Adoption of FHIR in ABDM and NHCX, and the Digital Personal Data Protection Rules, G.S.R. 846(E) (planning and technical context only; provider legal counsel, privacy officers, and quality leads must verify operative clauses and state-specific rules), dual-market healthcare engineering for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719 / HCL-H0715-2026) requires explicit mapping of every outpatient opd queue token orchestration and no-show overbooking sop checklist control gate to statutory evidence:
- United States Acute & Specialty Care Governance (`USD $` — HC-719): Under
CMS Conditions of Participation (42 CFR § 482.23, § 482.24, § 482.25),HIPAA Security Rule 45 CFR § 164.312(a)(1) & (b),ONC 21st Century Cures Act HL7 FHIR R4 US Core, andASC X12N 837I/837P & 835 ERAstandards, every episode inHCL-H0715-2026must preserve unique user authentication, tamper-evident audit trails, medical-necessity linkage (ICD-10-CM/PCStoCPT/HCPCS), and timely payer prior-authorization alignment to prevent$285CARC/RARCclaim denials and Recovery Audit Contractor (RAC) clawbacks. - Indian Multi-Specialty Hospital & Digital Health Governance (`INR ₹` — HC-719): Under
NABH 5th/6th Edition(Access, Assessment and Continuity of Care [AAC],Care of Patients [COP],Management of Medication [MOM], andInformation Management System [IMS]),ABDM Health Data Management Policyconsent artifacts (HIU/HIP),NHCXFHIR claim bundles,IRDAIcashless turnaround mandates, andPM-JAY / CGHS / ECHSpackage rules, 740-bed facilities must bind every clinical and financial artifact (Barcoded Vacutainer Chain-of-Custody,Critical Value Read-Back Log,Westgard QC Chart) to a permanentUHIDand verifiedABHAaddress so TPA assessors cannot disallow₹7,700package components at discharge.
GEO Citation Capsule (Clinical Custody & Payer Reconciliation): Across dual-market hospital operations for outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719), synchronizing Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log, and Westgard QC Chart between ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine enforces both US HIPAA 45 CFR § 164.312 / X12 837-835 claim integrity and India NABH 5th Edition / ABDM NHCX FHIR R4 compliance, eliminating 21.9% of pre-bill variance and protecting $137,655 USD (₹37.19 Lakhs INR) per year.
Timestamped Clinical Shift Incident Trace and Interlock Recovery
Bottom-Line Operational Rule: Testing outpatient opd queue token orchestration and no-show overbooking sop checklist resilience requires walking a concrete, timestamped shift incident trace to verify that out-of-tolerance events are intercepted at Gate D within seconds rather than discovered weeks later during payer remittance audits (HC-719).
The chronological 5-step operational trace below (Trace ID: TRC-H0715-09) illustrates how the Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719) control architecture intercepts a high-risk clinical-to-financial discrepancy during a live hospital shift across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine:
- 06:45 Shift Intake & Order Initiation (`Node A` — HC-719): During morning shift handover in the 740-bed facility, an urgent episode (
ENC-H0715-884) is initiated in ASTM/HL7 Bidirectional Analyzer Interface. The system validates the patient's permanentUHID, linksBarcoded Vacutainer Chain-of-Custody, and assigns a sequence lock (SEQ-719-01). - 08:12 Point-of-Care Execution & Custody Drift (`Node B` — HC-719): During high-acuity floor load, a secondary consumable/procedure modification is performed at the bedside, but the operator attempts to advance the worklist using a manual batch override without scanning the updated
Critical Value Read-Back Logbarcode lot/reference, creating a$285(₹7,700) unverified variance. - 08:13 Automated Three-Way Gate Interception (`Node C -> Gate D` — HC-719): Within
380 msof the attempted state transition, the stage-gate rules engine evaluatesDelta_Ep (HC-719), detects the mismatch betweenBarcoded Vacutainer Chain-of-Custodyand the unverifiedCritical Value Read-Back Logpayload, and evaluatesGate D = No. - 08:14 Quarantine Isolation & Owner Escalation (`Node E -> Node F` — HC-719): Instead of allowing the corrupted record to pollute LIS & Physician Alert Engine,
Node Eplaces a hard hold (HOLD-H0715-402) on discharge/claim finalization and dispatches a priority alert to Diagnostic Lab Director with a34-minuteSLA countdown. - 08:29 Primary Source Remediation & Verified Release (`Node F -> Node C -> Node G -> Node H` — HC-719): The unit supervisor scans the physical
Critical Value Read-Back Logcustody evidence atNode F, attaches the required clinical modifier toWestgard QC Chart, re-clearsGate D = Yesat 08:29 (15 minutestotal containment), and releases the cryptographically hashed episode packet toNode GandNode H.
Dual-Market Worked Financial and Operational Reconciliation Ledger
Bottom-Line Operational Rule: Every CFO and hospital operations director evaluating outpatient opd queue token orchestration and no-show overbooking sop checklist must reconcile physical episode volumes against a dual-market financial ledger in both United States Dollars (`USD $`) and Indian Rupees (`INR ₹`) to quantify prevented denials, reclaimed bed/modality capacity, and labor savings (HC-719).
In our 740-bed benchmark processing 850 monthly episodes (10200 annual episodes) for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719), the 161 monthly exceptions (21.9% baseline failure rate) generate three distinct financial drains: direct payer disallowances/denials on Westgard QC Chart, administrative rework labor (255 minutes per failed episode across nursing, MRD, coding, and TPA desks), and blocked bed or diagnostic slot turnover. Deploying the Node A–H stage-gate architecture in HCL-H0715-2026 reduces the residual exception rate to 1.50% and compresses resolution latency to 34 minutes:
Scroll horizontally to see all columns.
Financial & Operational Reconciliation Line (HCL-H0715-2026 / HC-719) | US Acute-Care Hospital (USD $ — CMS / X12 / ASC 606) | India Multi-Specialty Hospital (INR ₹ — NABH / NHCX / Ind AS 115) | Control Gate Mechanism & Verification Evidence |
|---|---|---|---|
| Monthly Episode Volume & Baseline Exception Cohort | 850/mo (161 exceptions @ 21.9%) | 850/mo (161 exceptions @ 21.9%) | Audited at Node C across Barcoded Vacutainer Chain-of-Custody and Critical Value Read-Back Log |
| Per-Episode Unverified Claim / Tariff Exposure | $285 USD per unverified episode | ₹7,700 INR per unverified episode | Prevented by hard pre-release scrub at Gate D on Westgard QC Chart |
| Monthly Rework Labor & Boarding/Slot Drag Recovered | $11,471 USD / mo (255m -> 34m) | ₹3,09,925 INR / mo (255m -> 34m) | Automated routing via Node E -> Node F SLA worklists |
| Net Annualized Margin & Revenue Protection | `$137,655 USD / year` | `₹37.19 Lakhs INR / year` | Reconciled at `Node G–H` with 100% SHA-256 audit traceability |
Deterministic EMR Control Gates Versus Bounded Healthcare AI Agents
Bottom-Line Operational Rule: Healthcare organizations must never delegate final clinical authorization, identity merging, or payer claim sign-off in outpatient opd queue token orchestration and no-show overbooking sop checklist to unconstrained generative AI; deterministic rules engines must govern Gate D, while AI agents operate strictly as bounded, read-only preparation copilots (HC-719).
When modernizing Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719 / HCL-H0715-2026), CIOs and CMIOs face aggressive vendor marketing claiming that autonomous AI agents can "automate end-to-end hospital operations." In regulated clinical and revenue-cycle environments across a 740-bed network, allowing a probabilistic Large Language Model (LLM) to autonomously mutate Barcoded Vacutainer Chain-of-Custody, override Critical Value Read-Back Log custody locks, or submit Westgard QC Chart claims creates severe patient-safety and False Claims Act / IRDAI audit liability. The table below defines the mandatory architectural separation between deterministic HIS/EMR control gates and bounded AI copilot assistance for outpatient opd queue token orchestration and no-show overbooking sop checklist:
Scroll horizontally to see all columns.
| Workflow Decision Domain in Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719) | Deterministic HIS / EMR / RCM Gate Authority (100% Rule-Bound) | Bounded AI Agent / Copilot Role (Advisory & Draft-Only) | Mandatory Human Sign-Off & Audit Trail |
|---|---|---|---|
| Patient Identity & Prior-Auth Binding (`Node A`) | Exact composite match on UHID, ABHA/MRN, encounter key & active policy | OCR extraction of scanned referral/payer documents into draft fields on Barcoded Vacutainer Chain-of-Custody | Registration lead or TPA desk verifies & commits (Node A) |
| Clinical & Custody Verification (`Node B–D`) | Hard mathematical & barcode lock (Delta_Ep == 0) on Critical Value Read-Back Log | Anomaly detection flagging unusual timestamp drift or missing lot attachments | Attending clinician, pharmacist, or lab head signs off at Node F |
| Coding, Tariff & Claim Scrubbing (`Node E–G`) | Deterministic X12 837 / NHCX and payer tariff-table validation on Westgard QC Chart | Suggesting candidate ICD-10 / CPT / package codes cited to chart sentences | Certified medical coder & billing controller approve release at Node G |
| Surveyor & Remittance Audit (`Node H`) | Immutable SHA-256 hash chain across Barcoded Vacutainer Chain-of-Custody, Critical Value Read-Back Log, and Westgard QC Chart | Natural-language search across archived audit packets for surveyor queries | Quality officer (NABH / Joint Commission) & CFO sign-off |
Scope & Applicability Boundary: This dual-layer deterministic-plus-bounded-AI architecture for outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719) is engineered for multi-specialty tertiary hospitals, multi-site clinic chains, and high-volume diagnostic networks operating across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine. Standalone single-clinician outpatient practices with fewer than 25 daily cash visits and no inpatient/TPA billing handoffs do not require automated HL7 FHIR message brokers or dedicated Node E quarantine queues.
Architecture Verification Checklist and Clinical Cutover Governance
Bottom-Line Operational Rule: Deploy outpatient opd queue token orchestration and no-show overbooking sop checklist controls across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine using a phased 30-60-90 day shadow-to-live rollout that validates negative-path quarantine holds in staging before enforcing hard blocks in live clinical units (HC-719).
To eliminate disruption to active patient care during implementation, Diagnostic Lab Director, LIS-HIS Integration Lead, NABH / Joint Commission Quality Officer should execute the following four-stage verification and rollout scorecard for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719 / H0715):
Scroll horizontally to see all columns.
| Rollout Phase & Milestone Window | Operational Scope & System Target | Negative-Path Stress Test Required | Go-Live Acceptance Gate Criteria |
|---|---|---|---|
| Days 1–15: Baseline & Schema Lock | Sample 100 historical episodes of outpatient opd queue token orchestration and no-show overbooking sop checklist across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine | Replay corrupted/incomplete Barcoded Vacutainer Chain-of-Custody and Critical Value Read-Back Log payloads in staging | 100% of synthetic exceptions caught by Delta_Ep (HC-719) rule |
| Days 16–30: Shadow Gate Telemetry | Run Node A–D rules in passive shadow mode on live hospital traffic | Measure false-positive hold rate across day, evening, and night shifts | Shadow false-positive rate tuned below 1.5% with role owners trained |
| Days 31–60: Flagship Unit Cutover | Enable active Gate D -> Node E quarantine holds in 1 flagship ward/unit | Inject duplicate barcode scan, missing pre-auth, and late timestamp drift | P90 Node E -> Node F containment <= 34 min; zero bypassed holds |
| Days 61–90: Network Lock & CQI | Expand across all 740 beds and lock monthly CQI / CFO ledger review | Full end-to-end drill from Node A intake to Node H surveyor packet export | First-pass yield >= 98.5% and verified $137,655 / ₹37.19L run-rate |
- Verification Check 1 (Initiation & Identity Integrity — HC-719): Confirm that ASTM/HL7 Bidirectional Analyzer Interface blocks any outpatient opd queue token orchestration and no-show overbooking sop checklist transaction lacking a valid
UHID, encounter ID, and linkedBarcoded Vacutainer Chain-of-Custody(HC-719). - Verification Check 2 (Custody & Telemetry Lock — HC-719): Verify that
Node Brequires contemporaneous barcode or instrument capture onCritical Value Read-Back Logand flags any back-entered timestamp drift exceeding 15 minutes (HC-719). - Verification Check 3 (Quarantine Routing & SLA Escalation — HC-719): Audit
Node EandNode Fto confirm that failed GateDchecks route immediately to Diagnostic Lab Director with a34-minuteescalation timer and mandatory loop back toNode C(HC-719). - Verification Check 4 (Subledger & Surveyor Closure — HC-719): Reconcile finalized
Westgard QC Chartpostings atNode GandNode Hagainst US X12 835 / India NHCX & TPA remittance ledgers at every shift close (HC-719).
Next actions
- Audit your last 100 episodes of outpatient opd queue token orchestration and no-show overbooking sop checklist (
HCL-H0715-2026/HC-719) across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine to quantify your baseline exception rate atGate DacrossBarcoded Vacutainer Chain-of-Custody,Critical Value Read-Back Log, andWestgard QC Chart. - Configure the deterministic quarantine loop (
D --No--> E -> F -> C) for Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook (HC-719) in staging so unverified records cannot advance toNode Gdischarge or billing settlement without supervisor remediation. - Establish a weekly 15-minute cross-functional review with Diagnostic Lab Director, LIS-HIS Integration Lead, NABH / Joint Commission Quality Officer tracking
HCL-H0715-2026first-pass reconciliation yield (target >= 98.5%) and P90 hold resolution latency (target <= 34 minutes).
Continue your evaluation
Request a 2–4 week healthcare workflow pilot focused on outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719) across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine.
Run a hospital software evaluation with real acceptance scenariosApplying this guide
The scenarios and numbers are illustrative. Confirm these provider-specific inputs before implementation:
- Diagnostic Lab Director: Signed stage-gate rule specification for outpatient opd queue token orchestration and no-show overbooking sop checklist (HC-719) verifying Barcoded Vacutainer Chain-of-Custody and Critical Value Read-Back Log custody locks across ASTM/HL7 Bidirectional Analyzer Interface to LIS & Physician Alert Engine.
- LIS-HIS Integration Lead: Reconciled HCL-H0715-2026 dual-market variance ledger confirming zero unverified Westgard QC Chart releases prior to Gate D clearance.
- NABH / Joint Commission Quality Officer: Verified HIPAA 45 CFR § 164.312(b), NABH 5th/6th Edition, and ABDM FHIR R4 immutable audit trail archival at Node H (HC-719).
Operational FAQs — People also ask
Concise answers to common evaluation and implementation questions on outpatient opd queue token orchestration and no-show overbooking sop checklist in healthcare operations.
What is the primary operational control rule for outpatient opd queue token orchestration and no-show overbooking sop checklist?
How should outpatient & ambulatory ops (maternity high-risk) teams handle exceptions and approval boundaries?
When should teams use deterministic ERP workflow rules versus AI agents for outpatient opd queue token orchestration and no-show overbooking sop checklist?
What is the safest way to evaluate or pilot changes for "Outpatient OPD Queue Token Orchestration And No-show Overbooking in Maternity And High-risk Obstetrics: Floor Exception SOPs & 90-Day Rollout Playbook"?
References
- NABH standards catalogue — Programme selection context only; obtain the current full applicable standard before clause-level assertions. Accreditation is distinct from law and software certification.
- NABH hospital accreditation standards, sixth edition — Planning context for hospital records and accountability; quality lead must verify applicable edition and programme scope.
- ABDM Health Data Management Policy — ABDM ecosystem role and consent context; check current policy version and separate clinical, data-processing and exchange consent.
- NRCeS ABDM FHIR Implementation Guide (v6.5.0) — Published FHIR R4 profile reference; pin the exact release and confirm partner conformance before production use.
- NRCeS Implementation Guide for Adoption of FHIR in ABDM and NHCX — Message and role boundaries for ABDM/NHCX adoption; verify current NHA onboarding and payer support.
- Bahmni feature list — Module boundary reference across registration, clinical services, lab, stock and billing; verify actual deployed version.
Topics: outpatient opd queue token orchestration and no-show overbooking sop checklist · maternity and high-risk obstetrics outpatient opd queue · outpatient opd queue token sop rollout playbook · healthcare outpatient & ambulatory ops


